

Current vascular treatment options can leave patients facing ongoing complications, repeated procedures and poor long-term outcomes.
Xeltis is developing medical devices designed to break this cycle by enabling the body to transform the implant into living, long-lasting tissue.
Today, Xeltis is focused on addressing these areas of high unmet need


Vascular access for end-stage renal disease patients requiring hemodialysis

Coronary arterial bypass surgery for cardiovascular disease patients

Peripheral arterial bypass surgery for peripheral arterial occlusive disease patients

Pulmonary heart valve for congenital heart malformations requiring valve replacement surgery
The Challenge
Hemodialysis access in end-stage renal disease patients
End-stage renal disease (ESRD) is a life-threatening condition that often requires lifelong hemodialysis treatment.
Hemodialysis access is not a ‘create and forget’ procedure. Vascular access must be created, maintained and often repeatedly restored to ensure reliable blood flow for dialysis. The burden on patients and healthcare systems continues to grow as the prevalence of chronic kidney disease increases worldwide.
-
850 million of kidney disease patients globally
-
5th leading cause of death globally by 2040
-
Less than 25% of patients survive five years following diagnosis
-
$140 billion spent on chronic kidney disease each year worldwide
-
$50 billion spent annually on dialysis treatment alone
-
3.5 million patients rely on routine hemodialysis every year
-
6% annual growth in the global dialysis patient population
To perform hemodialysis, reliable vascular access is essential. Today, patients typically receive a temporary catheter, arteriovenous fistula (AVF) or arteriovenous graft (AVG).
However, each option has significant limitations, including complications, repeat procedures and challenges in achieving long-term access durability.
aXessTM

CURRENT OPTIONS
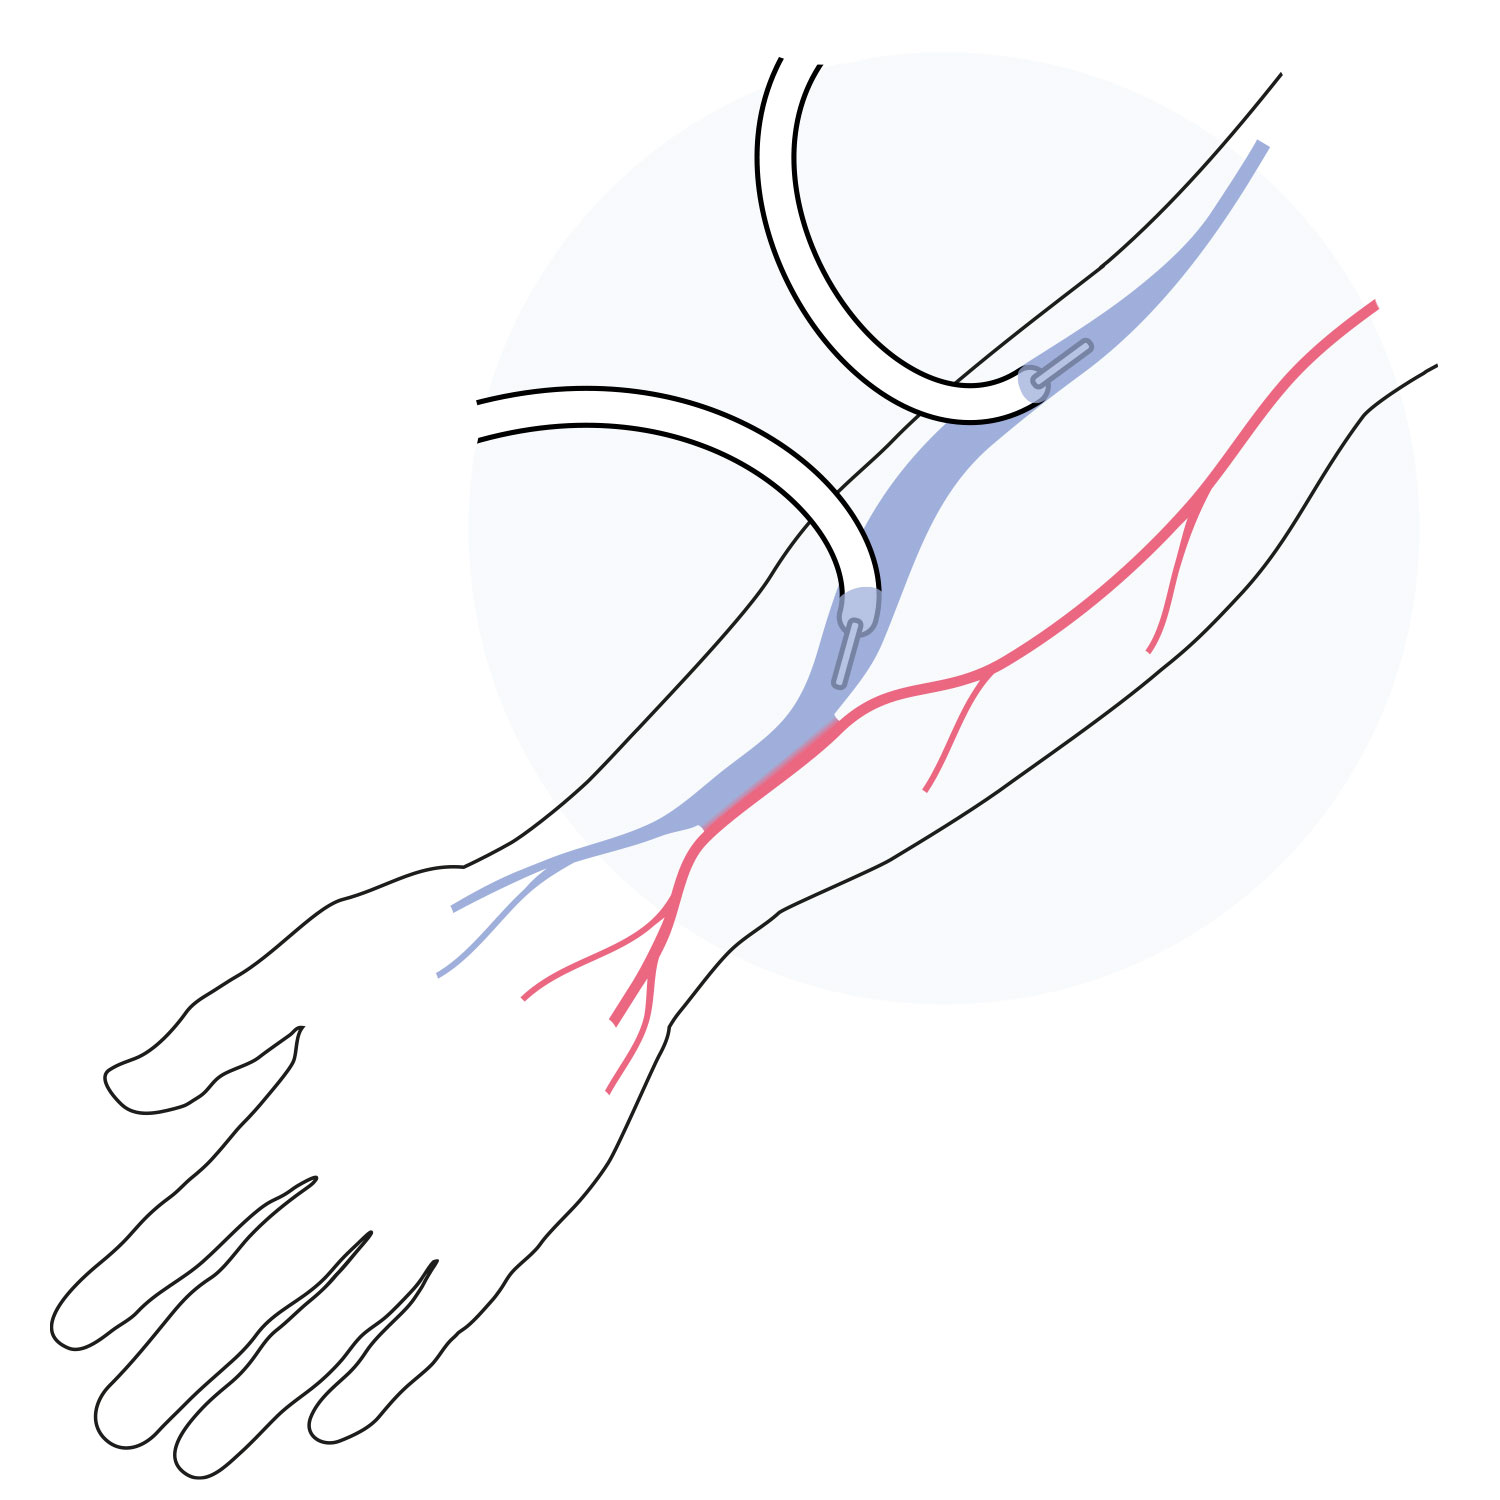
AVF
An arteriovenous fistula (AVF) is a passage created by joining and enlarging an artery and a vein in the patient’s arm.
It is generally a longer lasting option.
Disadvantages
- Takes time to develop or mature:
4 weeks to 4 months - Many fail to mature (up to 60%)
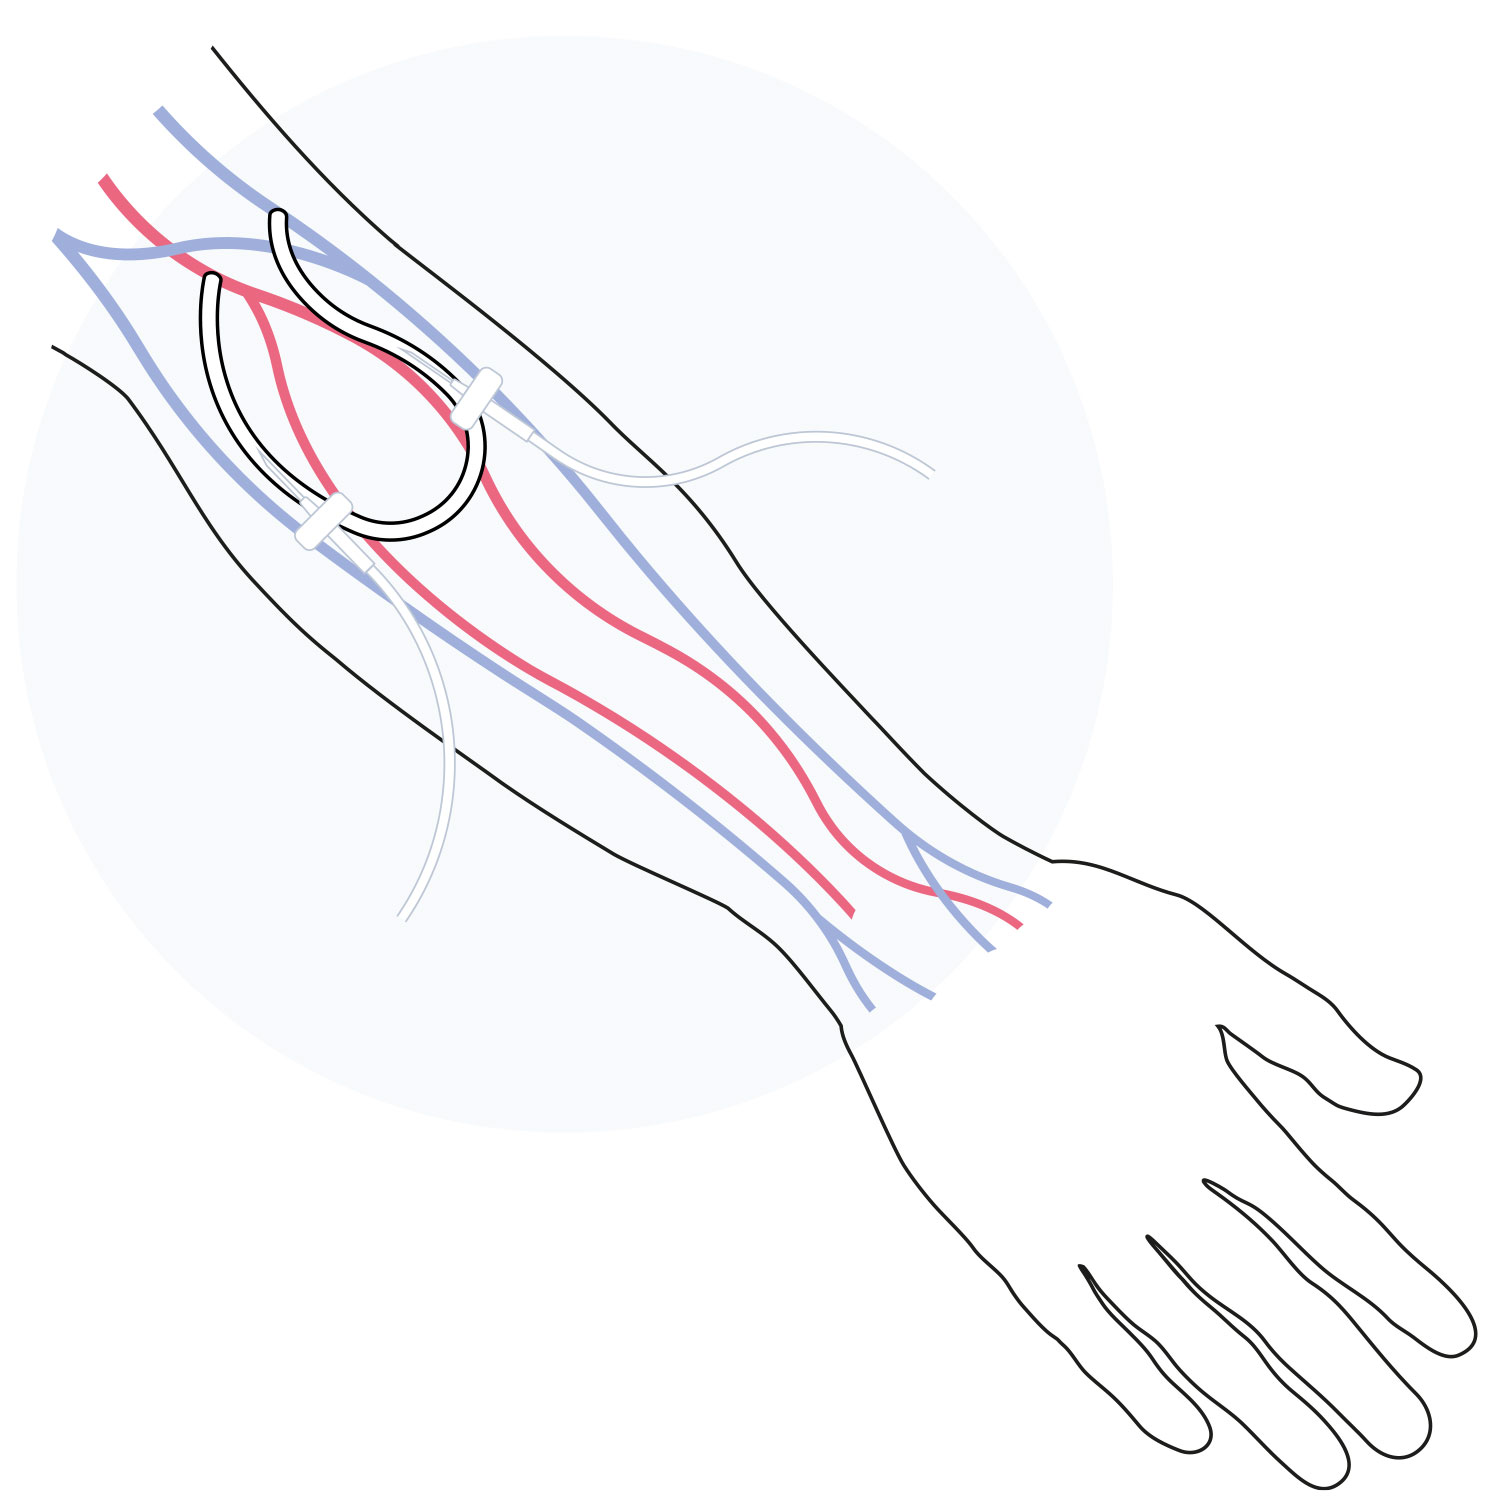
AVG
An arteriovenous graft (AVG) is a small plastic tube implanted in the patient’s arm to connect an artery and a vein.
Most grafts can be used between a few days and within three weeks after implanting.
Disadvantages
- Risk of occlusion and early abandonment
- Increases risk of infection and blood clot
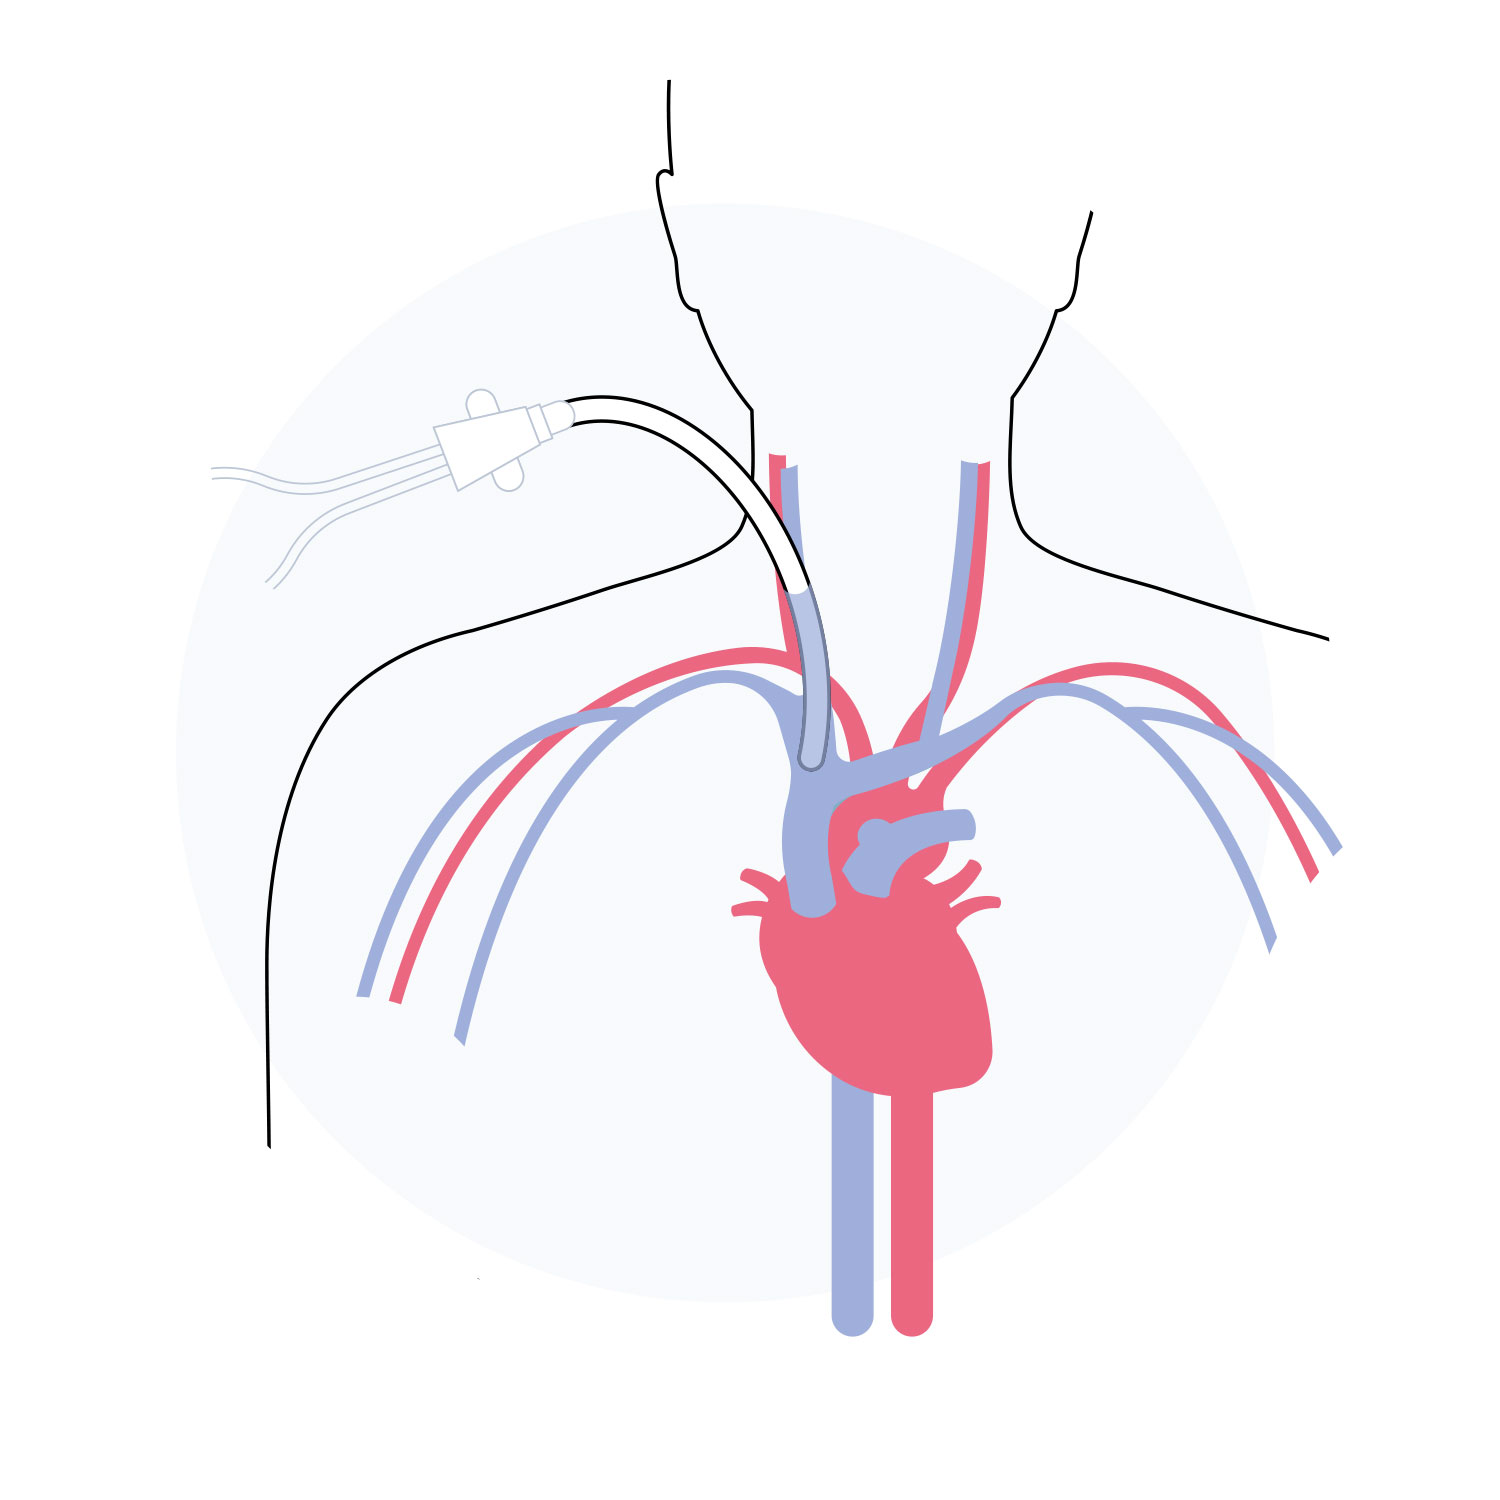
CVC
A central venous catheter (CVC) is a larger tube implanted in the patient’s neck to provide access to larger veins.
It provides immediate dialysis access.
Disadvantages
- Has more than 20% risk of infection, as its tip is located near the heart
24-month FIH data
- Excellent patency and safety profile
- Low reintervention rates
- 0% cannulation related infections
- Three times lower reintervention rate compared to standard ePTFE AVG’s
*As presented at Veith 2024 by Prof. Moll. Halbert et al. 2020
The Solution
aXess™ Vascular Access Implant
aXess™ is a restorative conduit which enables the creation of a new, long-term living vessel for hemodialysis vascular access.
It combines the safety and patency of a fistula with the speed to treatment of an AV graft. The aXess™ vascular access implant offers an improved experience for hemodialysis patients and reduces reinterventions, complications and infections.
A first-in-human trial of aXess™ demonstrated a significant improvement in performance compared to other hemodialysis vascular access solutions.
The EU pivotal trial completed its enrollment of 120 patients in more than 9 EU countries. The pivotal trial achieved its primary goal, confirming and building upon the results from the initial first-in-human study.
The findings demonstrated higher patency rates and reduced infection and intervention rates compared to the current standard of care.
aXess™ US pivotal trial is currently enrolling patients.
The Challenge
Coronary artery disease and bypass surgery
Coronary artery disease is a leading cause of cardiovascular death, linked to 17.9 million deaths each year, growing at a rate of 9% annually.
When coronary arteries become blocked, patients may require Coronary Artery Bypass Grafting (CABG) surgery to restore blood flow to the heart.
Key Facts
-
1 million CABG patients each year
-
20% of vein grafts fail within a year
-
75% of vein grafts fail within 10 years
-
40% suffer complications
-
€111 billion spent annually on cardiovascular disease in Europe
-
$318 billion spent annually on cardiovascular disease in the US
Current CABG procedures often require the removal of multiple veins from the leg, increasing surgical burden and the risk of complications.
This highlights the need for more durable and less invasive coronary bypass solutions.
The Solution
Xabg™ Coronary Artery Bypass Implant
Xabg™ is an implant based on the Nobel-Awarded science Restorex® supramolecular polymer, which transforms to the patient’s own vessel to enable continued blood flow in patients with coronary artery disease.
Xeltis’ solution has the potential to transform the bypass surgery landscape, eliminating the need for vein harvesting and its associated burden on patients and healthcare systems.
Proof-of-concept and preclinical trials have been completed in animals, demonstrating the implant to remain open 12 months, with healthy tissue regeneration in and around the vessel leading to long-term durability. First human trial data showed the implants remain patent at 1 year.
A first-in-human trial is underway. Click here to find out more.
The Challenge
Peripheral bypass surgery
Peripheral Artery Disease (PAD) affects more than 200 million people worldwide and can lead to severe pain, chronic wounds, limb loss, and loss of independence.
When arteries in the legs become severely blocked, patients may require bypass surgery to restore blood flow and preserve the limb.
Key Facts
-
>12 million Americans and >10 million Europeans affected by PAD each year
-
Incidence growing globally, with aging population at a higher risk
-
20% of vein grafts fail within one year
-
50% of prosthetic grafts fail within two years
-
Endovascular and surgical treatments show comparable outcomes
-
20% suffer from major adverse limb effects within one year, often requiring amputation
-
25% mortality rate at two years, higher rate in patients requiring amputation
-
300,000 hospitalizations andover $6 billion spent annually on PAD in the US
While endovascular treatments are widely used, bypass surgery remains the preferred option for many patients with complex disease, failed prior interventions, or a need for durable long-term outcomes.
However, current bypass procedures often rely on harvesting the patient’s own vein, creating limitations and highlighting the need for more durable and readily available vascular graft solutions.
The Solution
Xpad™ Peripheral Artery Bypass Implant
Xpad™ is an implant based on the Nobel-Awarded science Restorex® supramolecular technology, which transforms to the patient’s own vessel to enable continued blood flow in peripheral arteries above-the-knee and below-the-knee.
Xeltis’ solution has the potential to eliminate the need for vein harvesting and its associated burden on patients and healthcare systems.
XPAD clinical trial for peripheral arterial occlusive disease (PAOD) is ongoing.
FUTURE EXPANSIONS
The Challenge
Pulmonary heart valve replacement
Pulmonary heart valve disease affects around 30,000 patients per year. Many of them are children born with congenital heart defects.
1 in 5 pulmonary heart valves fail within a year
Current pulmonary valve replacement options have poor performance and can fail prematurely due to narrowing of the heart valve caused by stenosis, calcification and endocarditis, often leading to repeat interventions.
The Solution
Xplore-2 Pulmonary Heart Valve
Xplore-2 is a pulmonary heart valve implant which turns into the patient’s own living valve.
Made with Restorex® supramolecular polymer technology, Xplore-2 has the potential to significantly reduce the reintervention rate associated with current valve replacement devices, and the related burden on healthcare systems.
12-month clinical trial data showed no incidence of reoperation, reintervention or device-related death. Other trials are ongoing.
Visit xplore2md.com to learn more.
FREQUENTLY ASKED QUESTIONS
FAQ
What products are currently available or in development?
Current options for vascular replacements have significant limitations for patients, who often face a cycle of complications and reinterventions.
Xeltis aims to break this cycle by providing new, transformational treatment options. Xeltis’ current focus is on developing medical devices for several areas of high unmet need.
-
Vascular access for end-stage renal disease patients requiring hemodialysis – aXess™ now CE marked
-
Coronary artery bypass surgery for coronary artery disease patients Peripheral bypass surgery for patients with peripheral arterial occlusive disease (PAOD)
-
Pulmonary heart valve for patients with congenital heart malformations requiring valve replacement surgery
Which indications is Xeltis targeting?
The aXess™ Hemodialysis Conduit is indicated for patients with end-stage renal disease (ESRD) who require arteriovenous hemodialysis access in the upper extremities.
What stage of development is each program in?
aXess™ for hemodalysis treatment is now CE marked.
Xpad™ for peripheral arterial occlusive disease (PAOD) and Xabg™ for Coronary artery disease patients are in active human clinical trials.
What are the next clinical milestones?
aXess™ US pivotal trial has completed more than half of its enrolment. See PR announcement from July 2nd.
Xpad™ early feasibility and Xabg™ FIH clinical trials are ongoing.
Are there ongoing clinical trials?
aXess™ US pivotal trial is ongoing and progresses as planned.
aXess4All Post-market-surveillance trial is ongoing in European sites.
Xpad™ for peripheral arterial occlusive disease (PAOD) and Xbag™ for cardiovascular disease patients clinical trials are ongoing.
Where are Xeltis products approved or available?
aXess™ for hemodialysis treatment is CE marked, allowing its commercial availability in Europe.
When will Xeltis products be commercially available more broadly?
aXess™ US pivotal trial is ongoing, halfway enrollment milestone was completed in June 2026. Xeltis plans to seek FDA marketing authorization after completion of its US pivotal trial.
Which reimbursement pathways are being pursued?
Standard reimbursement for hemodalysis access creation applies to aXess™ in Europe.
aXess™ was granted Breakthrough Device Designation by FDA.
FAQ

What is aXess™?
aXess™ is a medical device for hemodialysis access.
The vascular access device is implanted in a single procedure, acting as a scaffold ready for cannulation and gradually transforming into each patient’s own living vessel for reliable, long-term access.
How does aXess™ work?
aXess™ is different by design. Built on Nobel Prize-winning science, the aXess™ device leverages Restorex® supramolecular electrospun polymer enabling the body’s natural healing. At implantation, the patient’s own cells infiltrate the porous aXess™ design, allowing instantaneous blood entrapment leading to fast hemostasis.
The implant allows for early cannulation with in 14 days. Overtime, a controlled transformation to the patient’s own living vessels is achieved for reliable access. Reducing infection risk, intervention burden and catheter dependency to positively impact patients’ quality of life. This has a positive shift on hemodialysis patient journey, toward a reliable living access and better quality of life.
What is the regulatory status of aXess™ in Europe and the US
aXess™ has received CE mark enabling commercialization across Europe.
In the United States, aXess™ FDA was granted Breakthrough Device Designation by FDA and is still an investigational device, limited by federal law to investigational use only, and not yet approved for commercial distribution.
How is aXess™ different from AV grafts or fistulas?
Unlike AV grafts, aXess™ is designed to be replaced by living tissue. aXess™ provides reliable hemodialysis access with fewer redos, and unlike fistulas, it provides a fast implantable solution allowing cannulation after 14 days.
When can aXess™ be used after implantation?
aXess™ is designed for early cannulation. The IFU currently recommend 14 days after implantation.
Who can benefit from aXess™?
ESRD patients requiring vascular access for hemodialysis.
What are the key benefits of aXess™?
aXess™ is designed to provide long-term clinical and economic benefits for patients and care teams by reducing infection risk, intervention burden and catheter dependency. aXess™ delivers these outcomes thanks to complementary layers of value with its design, manufacturing, clinical evidence, familiar implanting technique and life-long better economics.
Benefits include:
-
Reliable access as aXess™ transforms into each patient’s vessel. Infection resistance and fewer emergency interventions.
-
Lower reintervention burden, infection risk and catheter dependency. Delivering meaningful life-time cost saving, with up to €13k saving per patient on intervention devices, and up to €30k per each avoided blood stream infection.
-
Early cannulation (IFU recommends after 14 days)
-
Familiar implanting procedure, benefits of soft and strong material for ease of suturing, and fast hemostasis for predictable and time efficient dialysis sessions (in >95% of cannulations, hemostasis achieved in 5–10 mins.)[9]
What clinical evidence supports aXess™?
A substantial global body of evidence supports aXess™ clinical outcomes.
Recently Xeltis presented 12-month EU aXess™ pivotal multi-center trial with 120 patients; of which many complex patients [66% prior CVC, 34% prior AVF (17% with multiple attempts), 6% failed AVG].
Data demonstrates vs historical benchmarks:
-
Sustained vascular access performance – 79% secondary patency at 12 months, in line with matured AVF patency and better than AVG.[2]
-
Low infection rates – Clinically relevant access-related infection rate of ~3% per patient-year, comparable to 4% for arteriovenous fistulas (AVFs), 9% for arteriovenous grafts (AVGs) and 22% for central venous catheters (CVCs).[5]
-
Reduced reintervention rates – Up to 60% fewer reinterventions compared with standard synthetic grafts (AVGs) and up to 30% fewer vs matured arteriovenous fistulas (AVFs).[6]
How long does it take for the implant to transform to a natural tissue?
Post-implantation, aXess™ is a scaffold ready to cannulate and the transformation to a living vessel starts at implantation. You can see it. Blood immediately enters the porous Restorex® scaffold; fibrin and cells infiltrate and begin early tissue integration — supporting fast cannulation. IFU currently indicates cannulation can begin after 14 days.
Over time the polymer is gradually resorbed and replaced by the patient’s own tissue (largely resorbed over ~2 years based on preclinical sheep data), forming a living, compliant vessel.
For patients: How do I get aXess™?
In the EU aXess™ is now CE marked and is available in selected-sites, patients should consult their healthcare provider for access.
In the US aXess™ enrollment into its pivotal trial is ongoing. Patients can consult their healthcare provider to assess eligibility.
To learn more about the US clinical program go to usa.axesspivotal.com
usa.axesspivotal.com
Why is hemodialysis vascular access important?
Reliable vascular access is essential for effective hemodialysis treatment and significantly impacts patient outcomes and quality of life. Today Hemodialysis access is not a “create and forget” procedure.
It is a lifelong journey – for the patient, and for the care team behind them. Vascular access must be created, maintained and often repeatedly restored to ensure reliable blood flow for dialysis. aXess™ was designed to address these challenges.
Publications
FAQ

What is the Xeltis Xabg™ implant?
Xabg™ is an implant based on Nobel-Awarded science Restorex® supramolecular technology which transforms into Coronary Artery Bypass patient’s vessel to enable continued blood flow in coronary arteries. It has the potential to eliminate the need for vein harvesting and its associated burden on patients and healthcare systems.
Which patients is it intended for?
It is intended for patients requiring Coronary Artery Bypass.
What is its current clinical status?
The program is currently in clinical evaluation.
What makes Xeltis different from traditional vascular grafts?
Unlike traditional by-pass procedures, Xabg™ is designed to transform into living vessel to provide reliable blood flow to the heart. It has the potential to eliminate the need for vein harvesting and its associated burden on patients and healthcare systems.
FAQ

What is the Xeltis Xpad™ implant?
Xpad™ is an implant based on Nobel-Awarded science Restorex® supramolecular technology which transforms into each patient’s vessel to enable continued blood flow in peripheral arteries above-the-knee and below-the-knee.
Which patients is it intended for?
It is intended for patients requiring Peripheral Artery Bypass.
What is its current clinical status?
The program is currently in clinical evaluation.
What makes Xeltis different from traditional vascular grafts?
Unlike traditional by-pass procedures, Xpad™ is designed to transform into living vessel to provide reliable blood flow to the peripheral arteries.
Xeltis’ clinical programs are seeking to address the significant challenges faced by vascular surgery patients, offering transformative implants with reduced rates of infection, rejection and need for reintervention.
Visit our Patients page for an overview of our ongoing clinical trials.
Patients